CRISPR is powerful because it can aim. That is also why the rules matter
CRISPR is often sold as a molecular scissors story. The better question is where the scissors are aimed, who decides, and what happens if the cut is wrong.
Most arguments about CRISPR turn out to be arguments about three separate questions that have been collapsed into one: whose cells are being edited, whether the change can be inherited, and who signs it off. Held apart, the shouting gets quieter and the actual disagreements get easier to see. CRISPR systems can be designed to find particular DNA sequences and make changes there. That targeting ability is why the tool matters. It is also why context matters: editing cells in an adult patient is not the same as editing an embryo, editing a crop is not the same as editing a human, and a promising lab result is not the same as safe medical use. The tool can be precise, but the decision around it must be even more precise.
- CRISPR began as a bacterial defense system
- The guide is what gives the tool its aim
- Not all edits are the same
- Somatic editing and germline editing are ethically different
- Where CRISPR is already useful
- Off-target effects are only one safety issue
- The gene-edited baby case changed the public line
- Which kind of edit is this? A three-step triage
- Is there an approved CRISPR therapy my family could get?
- How to read a claim that CRISPR fixed a disease
- Here the hard question is whether we should
- Three shortcuts the coverage takes
- What would make us rewrite this page
- FAQ
This is for you if
- You want to understand CRISPR without hype or fear language.
- You want to know why somatic and germline editing are treated so differently.
- You want a checklist for reading gene-editing medical claims.
Skip this if
- You want personal genetic or medical advice.
- You need a lab protocol.
- You want a simple yes-or-no answer about all gene editing.
CRISPR began as a bacterial defense system
CRISPR systems were first understood as part of how bacteria remember and defend against viruses. Scientists adapted that natural targeting logic into a tool for editing DNA.
The common scissors metaphor is useful but incomplete. A CRISPR system needs a guide, a cutting or editing protein, a target sequence and a repair process. The edit is a chain of events, not one magic snip.
The guide is what gives the tool its aim
A guide RNA is designed to match a target DNA sequence. It helps bring the editing machinery to the right location. That address-like behavior is the heart of the technology.
Aiming is not perfect. Similar sequences elsewhere in the genome can raise off-target concerns. Delivery can be uneven. Cells can repair cuts in different ways. Precision is a goal measured by evidence, not a slogan.
Not all edits are the same
Some methods cut DNA and rely on repair. Others modify a base or prime an edit in a more controlled way. The field keeps developing tools meant to reduce unintended changes.
For a reader, the key is to ask what kind of edit is being described. CRISPR is a family label. The risk profile depends on the exact tool, target, cell type and delivery method.
Somatic editing and germline editing are ethically different
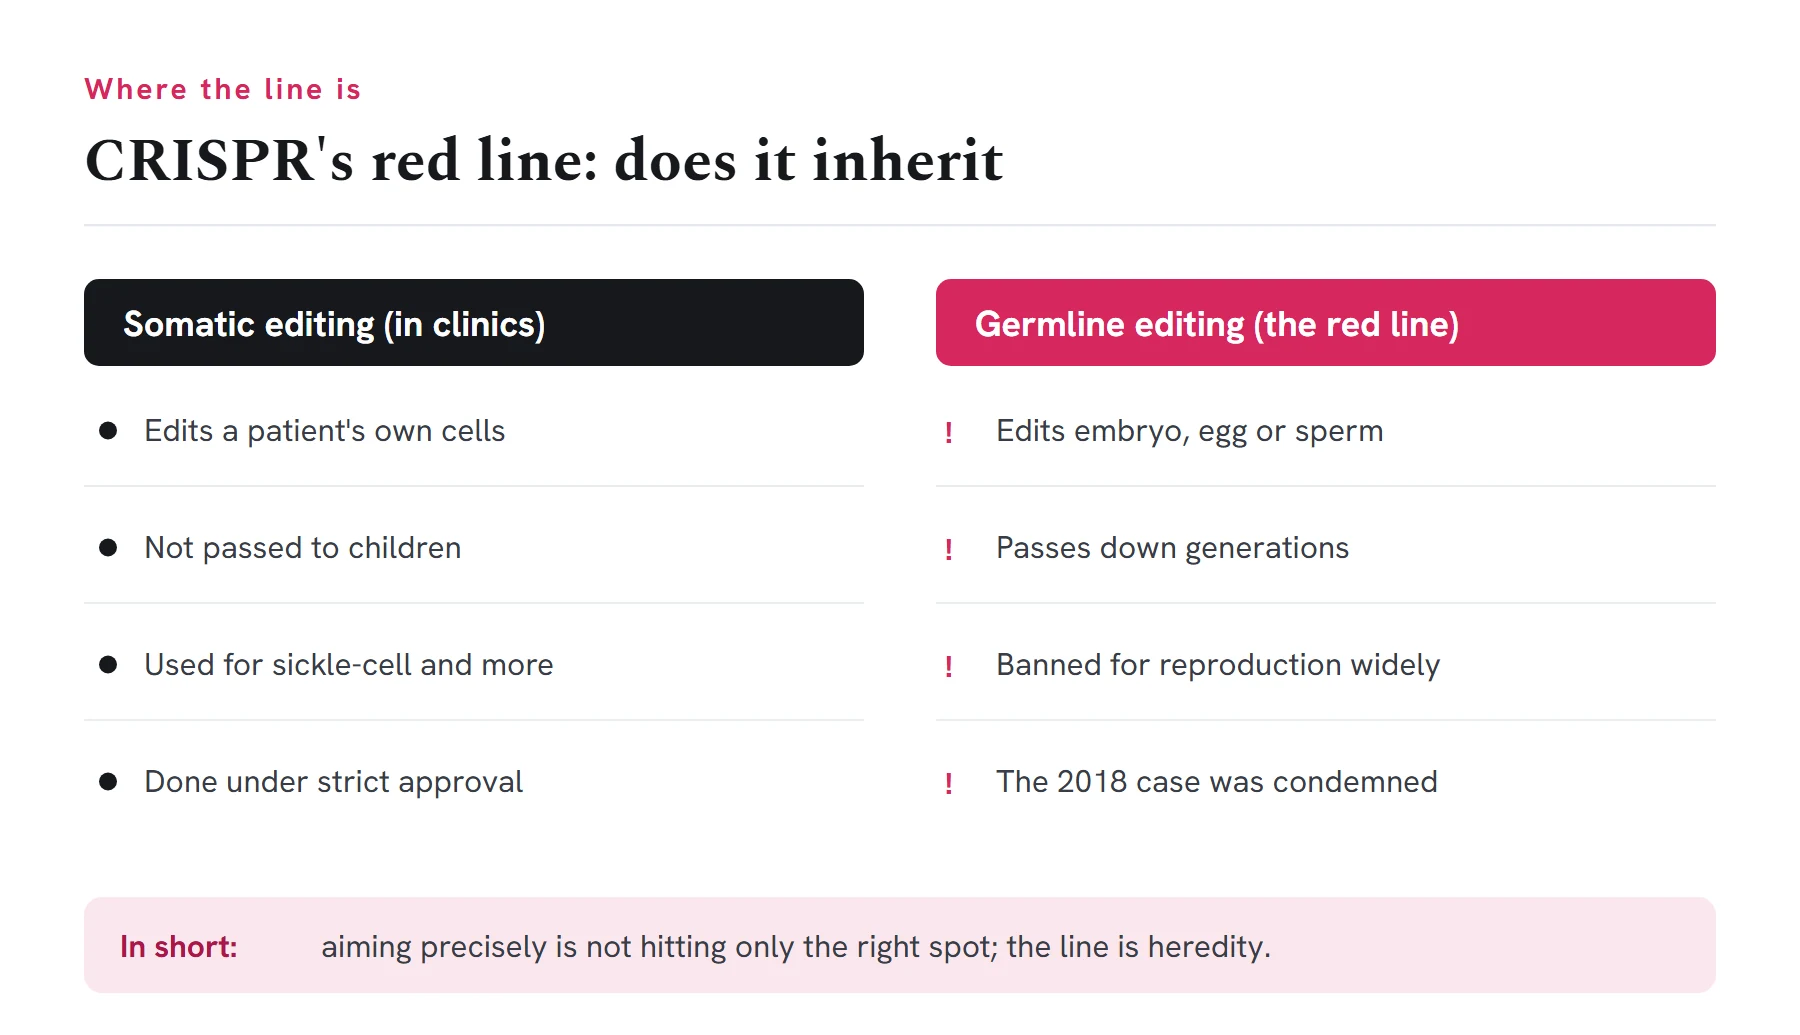
Somatic editing targets cells in an existing person and does not pass the change to future children. Germline editing changes embryos, eggs or sperm in a way that could be inherited. That line is why oversight becomes much more severe.
Medical risk is already serious for one patient. Heritable edits add consent problems for future generations and social concerns about enhancement, inequality and misuse. The difference is not technical only. It is moral and legal.
Where CRISPR is already useful
CRISPR is valuable in research because it lets scientists turn genes on, off or change them to learn what they do. It is also used in agriculture and in medical programs for certain genetic diseases.
The responsible claim is specific. Which disease, which cells, what delivery, what trial stage and what outcome? Broad statements like CRISPR cures disease hide the evidence you actually need.
Able to cut precisely is not the same as certain to cut only the right place. Treating the first as if it were the second is the optimistic trap that catches most readers of this kind of news.
Off-target effects are only one safety issue
Off-target edits matter, but safety also includes immune response, delivery risks, mosaicism, incomplete editing, long-term monitoring and whether the benefit justifies the intervention.
A therapy can be scientifically elegant and still too risky for a given disease if existing treatments are safer. Medicine judges the whole tradeoff, not just the cleverness of the edit.
The gene-edited baby case changed the public line
The case of babies born after embryo editing was widely condemned because it crossed ethical and safety boundaries before the science and oversight were ready. It remains a reference point because it shows what happens when capability outruns governance.
That case should not be used to freeze all research. It should be used to keep the bright line visible: heritable human editing demands extraordinary scrutiny and broad social agreement.
Which kind of edit is this? A three-step triage
Almost every argument about CRISPR turns out, on inspection, to be an argument about which case is on the table. Three questions, asked in this order, usually settle it before the ethics even start.
First: whose cells? If the edit is made in the cells of a person who already exists, and stays in those cells, it is somatic. It affects that patient and stops there. If it is made in an embryo, an egg or a sperm, it is heritable, and every objection about consent and irreversibility applies at once, because the people affected have not been born and cannot agree to anything. Nearly all clinical work sits on the somatic side. When a story does not tell you which one it means, that omission is itself information.
Second: repair or upgrade? Correcting a known variant that causes a defined disease is a different proposition from adding a trait somebody considers desirable. The first has a patient, a diagnosis and a measurable endpoint. The second has no patient and no endpoint, only a preference, and that is where the strongest objections live. Vague phrasing such as enhancing resilience is usually the second dressed up as the first.
Third: approved, in trial, or in a dish? A therapy cleared by a regulator, a therapy being tested in a small number of enrolled patients, and a striking result in cultured cells or in mice are separated by years and by most of the risk. Coverage routinely compresses all three into the word breakthrough. Ask how many humans have actually received it and the compression comes apart.
Of the three, the first does most of the work. Whose cells settles almost every genuinely contentious story on its own, and the other two are usually answered somewhere in the second half of the article anyway. If only one of them is going to stick, make it that one.
Is there an approved CRISPR therapy my family could get?
Yes, for two inherited blood disorders. The first licensed CRISPR medicine is Casgevy (exagamglogene autotemcel), from Vertex Pharmaceuticals and CRISPR Therapeutics. The UK regulator, the MHRA, authorised it in November 2023. The US FDA approved it on December 8, 2023 for sickle cell disease in people 12 and older with recurrent vaso-occlusive crises, and on January 16, 2024 for transfusion-dependent beta thalassemia. In July 2026 the FDA extended both uses to children from age 2.
It is not a prescription you collect. Doctors take the patient’s own blood stem cells, edit them in a lab, give high-dose chemotherapy to clear the bone marrow, then infuse the edited cells once. Patients are followed in a long-term study afterwards. In the US it is given only at authorised treatment centres, more than 75 of them in July 2026, and the list price at approval was $2.2 million for one course. Ask the centre how insurance coverage works before anything starts.
For other conditions, CRISPR treatments are still experimental, and the way in is a clinical trial.
- Search ClinicalTrials.gov: put the condition in “Condition/disease”, add “CRISPR” or “gene editing” under “Other terms”, and change Study Status from “All studies” to “Recruiting and not yet recruiting studies”. Each record lists locations and contacts.
- Take the record number, which starts with NCT, to your specialist. Eligibility usually turns on the exact diagnosis and genetic variant, which your own doctor can confirm.
- Walk away from anyone selling “gene editing” for cash outside a registered trial or an approved product. A real trial has a registry number you can look up.
Questions to ask the specialist:
- Am I, or is my child, eligible for an approved therapy? If not, which trials fit?
- What does the conditioning chemotherapy involve, how long is the hospital stay, and what does it mean for fertility?
- How have patients with my diagnosis done, and for how long have they been followed?
- What happens if the edit does not take, and what are the alternatives, such as a stem cell transplant from a matched donor?
Trials can also be stopped for safety. In October 2025 the FDA put Intellia’s two late-stage trials of an in-body CRISPR therapy for transthyretin amyloidosis on hold after a patient had a serious liver reaction; the patient later died, and the hold on one of the two trials was lifted in January 2026. Ask any trial team how it watches for problems like that.
How to read a claim that CRISPR fixed a disease
First ask whether the data are from cells, animals or humans. Then ask how many patients, how long they were followed and what outcome was measured. A biomarker improvement is not the same as long-term clinical benefit.
Also ask what was not reported: side effects, durability, comparison group and access. A press release may highlight the best signal and leave the hard questions for the paper.
Here the hard question is whether we should
CRISPR makes some edits possible. It does not answer which edits are acceptable. The stronger the tool, the more important the boundary: therapy before enhancement, patient benefit before spectacle, evidence before marketing.
A careful public conversation should leave room for lifesaving medicine while refusing shortcuts around consent, safety and equity. That is not anti-science. It is how powerful science stays legitimate.
It also helps to separate editing from delivery. A precise editing tool is only useful if it reaches the right cells in enough of the body and avoids the wrong ones. Blood cells, liver cells, eye tissue and embryos raise different delivery and oversight questions. The word CRISPR can hide that practical difference unless the article tells you where the edit happens.
A sober claim also names the monitoring plan. Editing is not finished when the edit is made. Patients, crops or study systems may need follow-up to learn whether the change behaves as expected over time.
| Edit type | Where it acts | Why it matters |
|---|---|---|
| Somatic cell editing | Cells in an existing person | May treat disease without inheritance |
| Germline editing | Embryo, egg or sperm | Changes could pass to future generations |
| Research editing | Cells or model organisms | Helps learn gene function |
| Agricultural editing | Plants or animals | May change traits, with regulatory review |
| Enhancement claims | Traits beyond disease treatment | Raises major ethical and social concerns |
- Identify whether the edit is somatic or heritable.
- Look for human trial data, not only cell or animal results.
- Check follow-up time, side effects and durability.
- Be skeptical of miracle-cure wording and vague patient stories.
Three shortcuts the coverage takes
It can be targeted, but delivery, repair and off-target risk still matter.
Editing adult cells for disease is different from heritable embryo editing.
Biology is networked. Benefit and risk must be tested.
What would make us rewrite this page
A piece like this is a snapshot of a field that keeps moving, so it is worth saying plainly what would change the conclusions instead of letting them quietly go stale.
The clearest trigger would be long-term follow-up data on the somatic therapies already approved. Today the case for them rests on relatively short observation of small groups. Years of durability data, good or bad, would move this page more than any new editing technique would. A serious safety signal in that follow-up would tighten every paragraph here; a clean decade would loosen several of them.
A second would be a jurisdiction openly licensing heritable editing inside a regulatory framework, rather than somebody simply breaking the rules. That would turn this from an ethics question with a broad consensus into a policy question with visible disagreement, and the section on the red line would have to be rewritten to describe a live argument instead of a settled one.
A third would be delivery getting solved. Much of the caution here is not about aim at all; it is about getting the tool into enough of the right cells inside a living body. If that stops being the bottleneck, the list of realistically treatable conditions grows quickly, and several statements here about narrow applicability would need revising.
None of the three has happened as of this update. If you are reading long afterwards and none of them has appeared in the coverage you have seen, the picture described here probably still roughly holds.
FAQ
Does CRISPR create designer babies?
Heritable enhancement is exactly the area that raises the strongest ethical and safety objections. It is not a normal medical use.
Can CRISPR cure every genetic disease?
No. Disease biology, delivery and risk differ widely.
What is off-target editing?
An unintended change at a DNA location similar to the intended target.
Is this medical advice?
No. It is a technology explanation. Patients should speak with qualified clinicians.
Is a result in mice close to a treatment?
Usually not. Mouse work sits at the third step of the triage above, separated from an approved therapy by years, by delivery problems and by most of the safety risk.
Is there an approved CRISPR treatment?
Yes. Casgevy treats sickle cell disease and transfusion-dependent beta thalassemia. It was authorised in the UK in November 2023 and approved in the US in December 2023 and January 2024, is given only at authorised treatment centres, and had a US list price of $2.2 million at approval.
How do I find a CRISPR clinical trial?
Search ClinicalTrials.gov with your condition, add CRISPR or gene editing under Other terms, set Study Status to Recruiting and not yet recruiting studies, and take the NCT number to your specialist.
Sources & further reading
- nih.gov: Public biomedical research information.
- broadinstitute.org: CRISPR research background and educational material.
- nature.com: Research coverage on gene editing science and ethics.
Updated: May 20, 2026. A three-step triage and a note on what would change these conclusions were added on September 8, 2026. On September 29, 2026 we added the approved CRISPR therapy Casgevy, how it is given and what it costs, how to search for a trial, and questions to ask a specialist.

Fang Yu is the editor of FutureLens, turning published papers, official materials and public explanations into plain-language notes. He is most interested in the gap between a technology's public pitch and the evidence a careful reader can actually check. More about the author